
Note: This article is for general educational purposes only. Neutropenia can become serious quickly, especially when fever appears. Anyone with a low neutrophil count, cancer treatment history, recurrent infections, or a fever should contact a qualified healthcare professional promptly.
Neutropenia sounds like the name of a tiny distant planet, but it is actually a blood condition that can make everyday germs feel like overachievers. In simple terms, neutropenia means the body has too few neutrophils, a type of white blood cell that helps fight bacteria and fungi. Neutrophils are part of the immune system’s first-response team. When they are low, the body may have a harder time controlling infections before they become serious.
The tricky part? Neutropenia often does not announce itself with flashing lights. Many people feel completely normal until a routine blood test finds a low absolute neutrophil count, often called ANC. Others discover it after repeated infections, mouth sores, fevers, or during cancer treatment monitoring. The condition can be mild and temporary, or it can be severe and require urgent care. Like a smoke alarm, the number itself matters, but the situation around it matters even more.
This guide explains what neutropenia is, why it happens, how doctors diagnose it, what treatment may involve, and how people can live more safely while their immune defenses are temporarily understaffed.
What Is Neutropenia?
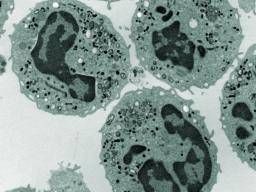
Neutropenia is a lower-than-normal level of neutrophils in the blood. Neutrophils are made in the bone marrow and released into the bloodstream, where they travel to tissues and help attack invading bacteria and fungi. They are not glamorous, but they are essential. Think of them as the immune system’s sanitation crew, security guards, and emergency responders rolled into one very busy cell type.
Doctors usually measure neutrophils with a complete blood count, or CBC, with differential. The key number is the absolute neutrophil count. In many clinical settings, neutropenia is often described by severity:
- Mild neutropenia: ANC about 1,000 to 1,500 cells per microliter
- Moderate neutropenia: ANC about 500 to 1,000 cells per microliter
- Severe neutropenia: ANC below 500 cells per microliter
These categories help estimate infection risk, but they do not tell the whole story. A person with mild chronic neutropenia may stay healthy for years, while someone with sudden severe neutropenia after chemotherapy may need immediate medical attention if fever develops. Duration, cause, symptoms, age, medications, and other health conditions all change the level of concern.
Why Neutrophils Matter
Neutrophils are especially important for fighting bacterial infections. When the body senses infection, neutrophils rush toward the problem, surround germs, release germ-killing substances, and help trigger inflammation. In a person with enough neutrophils, early infections may be contained quickly. In someone with severe neutropenia, infections can spread faster and sometimes produce fewer obvious warning signs.
That last point is important. Inflammation causes many classic infection symptoms, such as redness, swelling, pus, and warmth. When neutrophils are very low, those signs may be subtle or missing. Fever may be the only early clue. That is why healthcare teams take fever seriously in people with neutropenia, particularly cancer patients receiving chemotherapy.
Common Causes of Neutropenia
Neutropenia is not one disease with one cause. It is a blood-count pattern that can result from many different problems. Doctors usually think about causes in three broad buckets: the bone marrow is not making enough neutrophils, neutrophils are being destroyed too quickly, or neutrophils are being redistributed or used up during illness.
1. Cancer Treatment and Chemotherapy
Chemotherapy is one of the best-known causes of neutropenia. Many chemotherapy drugs target rapidly dividing cells. Cancer cells divide quickly, but so do healthy bone marrow cells that produce blood cells. When chemotherapy slows bone marrow activity, neutrophil levels can drop.
This type is often called chemotherapy-induced neutropenia. It may appear several days after treatment and may be monitored closely with repeat blood tests. For some patients, the count recovers before the next treatment cycle. For others, doctors may adjust chemotherapy timing, reduce a dose, prescribe growth factor medicine, or use infection-prevention strategies.
2. Infections
Some infections can temporarily lower neutrophil counts. Viral infections are common culprits. The body may use neutrophils rapidly, or the infection may temporarily suppress bone marrow production. Severe infections can also consume immune cells faster than the marrow can replace them.
In many cases, infection-related neutropenia improves as the illness resolves. However, persistent or severe neutropenia needs careful evaluation, especially when fever, fatigue, swollen lymph nodes, weight loss, or repeated infections are present.
3. Medications
Several medicines can rarely trigger neutropenia. This may happen through direct marrow suppression or an immune reaction that destroys neutrophils. Drug-related neutropenia can occur with some antibiotics, antithyroid medicines, anticonvulsants, antipsychotics, anti-inflammatory drugs, and other prescriptions. This does not mean people should panic and throw their medicine cabinet into the ocean. It means unexplained neutropenia should prompt a careful medication review with a clinician.
4. Autoimmune Conditions
Autoimmune neutropenia happens when the immune system mistakenly targets neutrophils. It may occur on its own or alongside conditions such as lupus, rheumatoid arthritis, inflammatory bowel disease, or other immune disorders. In children, some forms of autoimmune neutropenia can improve over time. In adults, the course depends on the underlying condition and severity.
5. Nutritional Deficiencies
The bone marrow needs the right raw materials to make healthy blood cells. Low vitamin B12, folate, or copper can contribute to neutropenia, often along with other blood-count changes such as anemia. This is one reason doctors may order nutritional labs when neutropenia is unexplained.
6. Bone Marrow Disorders
Because neutrophils are produced in the bone marrow, marrow disorders can cause low counts. Examples include aplastic anemia, myelodysplastic syndromes, leukemia, lymphoma involving the marrow, myelofibrosis, or marrow damage from radiation or toxins. These causes are less common than temporary viral or medication-related causes, but they are important to rule out when neutropenia is persistent, severe, or accompanied by low red blood cells or platelets.
7. Congenital and Cyclic Neutropenia
Some people are born with genetic conditions that affect neutrophil production or function. Severe congenital neutropenia may appear early in life with frequent infections. Cyclic neutropenia causes neutrophil counts to rise and fall in a repeated pattern, often every few weeks. During low-count periods, people may develop fevers, mouth ulcers, sore throat, or infections.
8. Benign Ethnic or Familial Neutropenia
Some healthy people naturally have lower neutrophil counts without having more infections. This is sometimes called benign ethnic neutropenia or benign familial neutropenia, depending on the context. The key word is “benign,” but that label should be applied by a healthcare professional after considering symptoms, history, and lab patterns.
Symptoms of Neutropenia
Neutropenia itself may cause no symptoms. The symptoms people notice usually come from infections that develop because neutrophil defenses are low. Possible warning signs include:
- Fever or chills
- Sore throat
- Mouth ulcers or gum inflammation
- Skin redness, swelling, tenderness, or sores
- Burning or pain with urination
- Cough, shortness of breath, or chest discomfort
- Abdominal pain or diarrhea
- Unusual fatigue with signs of illness
In severe neutropenia, fever is a red-alert symptom. A person with known neutropenia should not “wait and see” with a fever, especially if they are receiving chemotherapy, have a central line, recently had a transplant, or have other immune suppression. This is not the moment for heroic optimism and herbal tea alone. It is the moment to call the care team or seek urgent medical care.
How Neutropenia Is Diagnosed
Complete Blood Count With Differential
The first step is usually a CBC with differential. This test measures white blood cells, red blood cells, hemoglobin, platelets, and the different types of white blood cells. The differential allows the clinician to calculate the absolute neutrophil count.
A single low result may not be enough to diagnose a long-term problem. Neutrophil levels can fluctuate from day to day. Doctors often repeat the test to confirm the pattern, especially if the person feels well and the count is only mildly low.
Medical History and Physical Exam
Numbers matter, but context is king. A clinician will ask about recent infections, fevers, mouth sores, weight loss, night sweats, medications, supplements, chemotherapy, radiation, autoimmune symptoms, family history, alcohol use, diet, travel, and exposure risks. The physical exam may focus on the mouth, skin, lymph nodes, abdomen, spleen, lungs, and any possible infection sites.
Additional Blood Tests
Depending on the situation, doctors may order tests for vitamin B12, folate, copper, liver and kidney function, inflammatory markers, autoimmune antibodies, viral infections, or immune-system abnormalities. If medication-related neutropenia is suspected, the medication list becomes a detective board, minus the dramatic music.
Peripheral Blood Smear
A peripheral smear lets specialists look at blood cells under a microscope. It can reveal abnormal cell shapes, immature cells, or clues that suggest bone marrow stress, leukemia, nutritional deficiency, or other disorders.
Bone Marrow Examination
A bone marrow biopsy is not needed for every person with neutropenia. It may be recommended when neutropenia is severe, unexplained, persistent, associated with other abnormal blood counts, or concerning for marrow disease. The test helps show whether the marrow is producing neutrophils normally and whether abnormal cells are present.
Treatment for Neutropenia
Treatment depends on the cause, severity, duration, symptoms, and infection risk. There is no universal “neutropenia pill” that fits everyone. The best plan is targeted, like a good playlist and unlike a hospital gown, which fits no one perfectly.
Treating the Underlying Cause
If neutropenia is caused by a medication, the clinician may stop, replace, or adjust the drug when safe. If a nutritional deficiency is present, supplementation may help. If an autoimmune disease is driving the problem, treating that disease may improve the neutrophil count. If chemotherapy is the cause, the oncology team may adjust the treatment schedule or add supportive therapy.
Antibiotics and Antifungal Treatment
When neutropenia is accompanied by fever, clinicians often treat it as a medical urgency. Febrile neutropenia may require blood cultures, examination for infection sources, and prompt broad-spectrum antibiotics. Some high-risk patients need hospital care and intravenous medication. Lower-risk patients may sometimes be treated as outpatients, but only after careful medical assessment.
Growth Factor Therapy
Granulocyte colony-stimulating factor, often shortened to G-CSF, is a medication that encourages the bone marrow to make more neutrophils. It may be used for certain chemotherapy patients, severe chronic neutropenia, congenital neutropenia, or recurrent infection risk. It is not necessary for every case, and the decision depends on individual risk.
Changes to Cancer Treatment
For people receiving chemotherapy, neutropenia may lead to treatment delays, dose changes, or preventive growth factor injections. The goal is to protect the patient from infection while still treating the cancer effectively. This balance is delicate, so patients should avoid changing or skipping cancer treatment without medical direction.
Hospital Care for Severe Cases
Severe neutropenia with fever, low blood pressure, confusion, breathing problems, uncontrolled infection, or other warning signs may require hospitalization. In the hospital, care can include intravenous antibiotics, fluids, monitoring, imaging, cultures, and specialist consultation.
How to Reduce Infection Risk
People with neutropenia can take practical steps to lower infection risk. These habits are not glamorous, but neither is a preventable infection.
- Wash hands often with soap and water or use hand sanitizer when appropriate.
- Avoid close contact with people who are sick.
- Keep cuts clean and covered.
- Use a soft toothbrush if gums are tender.
- Follow food-safety guidance, especially during severe neutropenia.
- Avoid raw or undercooked meat, seafood, and eggs if the care team recommends a neutropenic diet approach.
- Ask before gardening, cleaning litter boxes, or handling soil during high-risk periods.
- Stay up to date on vaccines as recommended by a healthcare professional.
- Call the care team promptly for fever or infection symptoms.
Not every person with mild neutropenia needs strict lifestyle restrictions. Overdoing precautions can create unnecessary stress. The smartest approach is risk-based: ask the clinician what level of caution fits the actual ANC, medical history, and treatment plan.
When to Seek Medical Help
People with known neutropenia should ask their healthcare team what temperature counts as urgent and what number to call after hours. In many cancer-care settings, fever in neutropenia is treated as urgent because infections can progress quickly.
Seek immediate medical care for fever, chills, shortness of breath, chest pain, confusion, severe weakness, painful urination, severe abdominal pain, persistent vomiting or diarrhea, redness around a catheter, or any rapidly worsening symptoms. When in doubt, call. The immune system is not a great place to practice “maybe it will be fine” energy.
Living With Neutropenia: Practical Experience and Real-World Lessons
Living with neutropenia is often less about memorizing medical terms and more about building calm, repeatable habits. Many people describe the first low neutrophil result as confusing. The word looks intimidating, the numbers feel mysterious, and suddenly everyone is talking about germs as if a doorknob has become a supervillain. The good news is that daily life can often continue, especially with mild or temporary neutropenia, but it helps to understand your personal risk level.
One useful experience-based lesson is to keep a simple health log. Write down CBC dates, ANC results, infections, fevers, new medications, chemotherapy cycles, and symptoms such as mouth sores or sore throat. This turns vague memory into useful information. Instead of telling your doctor, “I think I was sick sometime after that one appointment near the rainy week,” you can say, “My ANC was 700 on May 3, I developed a fever on May 5, and I started antibiotics that evening.” Doctors love clarity. It saves time, reduces guesswork, and makes you look like the CEO of your own bloodstream.
Another lesson is to prepare before a fever happens. People at higher risk should know the exact fever threshold their healthcare team uses, which emergency department to visit, whether they should avoid taking fever reducers before calling, and what information to bring. A small “neutropenia plan” on the phone can help: diagnosis, medications, allergies, oncologist or hematologist contact, recent ANC, and treatment dates. During a stressful moment, this beats rummaging through papers while feeling terrible.
Food safety is another area where real life meets medical advice. Some patients become afraid of nearly every food, which can make eating miserable. Others ignore precautions completely and treat raw seafood like a personality trait. A balanced approach works better. Wash produce well, cook meats thoroughly, avoid questionable leftovers, check expiration dates, and follow the specific guidance from your care team. If your neutropenia is mild and chronic with no infection history, your rules may be different from someone in the high-risk window after chemotherapy.
Social life also requires judgment, not isolation forever. During high-risk periods, it may be wise to avoid crowded indoor spaces, sick visitors, or children with mystery sniffles. That does not mean disappearing from humanity. Video calls, outdoor meetups, masks when appropriate, and honest communication can help. A simple line works well: “My immune system is low right now, so I’m being careful about infections.” No dramatic speech required.
Oral care deserves special attention. Mouth sores and gum irritation can become infection entry points. A soft toothbrush, gentle flossing if approved, alcohol-free mouth rinses, and prompt reporting of mouth pain can make a difference. People receiving chemotherapy should ask about mouth-care routines before problems start.
Emotionally, neutropenia can feel unfair because it is invisible. You may look fine while being told to treat fever like an emergency. Family members may not understand why “just a cold” matters. Clear communication helps. Explain that low neutrophils reduce the body’s ability to fight certain infections quickly. You are not being dramatic; you are being medically practical.
The biggest takeaway from real-world experience is this: neutropenia management works best when it is personalized. Know your ANC trend, know your trigger symptoms, know your emergency plan, and know which precautions actually apply to you. With the right plan, neutropenia becomes less like a scary mystery and more like a condition you can monitor, discuss, and manage with confidence.
Conclusion
Neutropenia means the body has fewer neutrophils than expected, which can increase the risk of bacterial and fungal infections. It may be mild and temporary, or severe and urgent. Causes range from viral infections and medications to chemotherapy, autoimmune disease, nutritional deficiencies, congenital conditions, and bone marrow disorders.
Diagnosis usually begins with a CBC with differential and repeat testing, followed by a careful review of symptoms, medications, medical history, and sometimes additional blood tests, a smear, or bone marrow evaluation. Treatment depends on the cause and may include monitoring, correcting deficiencies, changing medications, treating infections, using antibiotics, giving G-CSF, or adjusting cancer therapy.
The most important practical message is simple: fever with significant neutropenia needs prompt medical attention. For daily life, good hygiene, food safety, symptom awareness, and a clear care plan can reduce risk without turning life into a bubble-wrap exhibit. Neutrophils may be tiny, but knowing how to protect them is a big deal.













